FDA-Cleared Indication
Tier A — FDA 510(k)-Cleared. Medicinal leeches (Hirudo medicinalis and H. verbana) are FDA-cleared via 510(k) — original clearance K040187, June 21, 2004 — as Unclassified Pre-Amendment devices (FDA product code NRN) for the management of venous congestion in tissue flaps and replantation surgery. This is the only FDA-cleared indication for medicinal leeches in the United States.
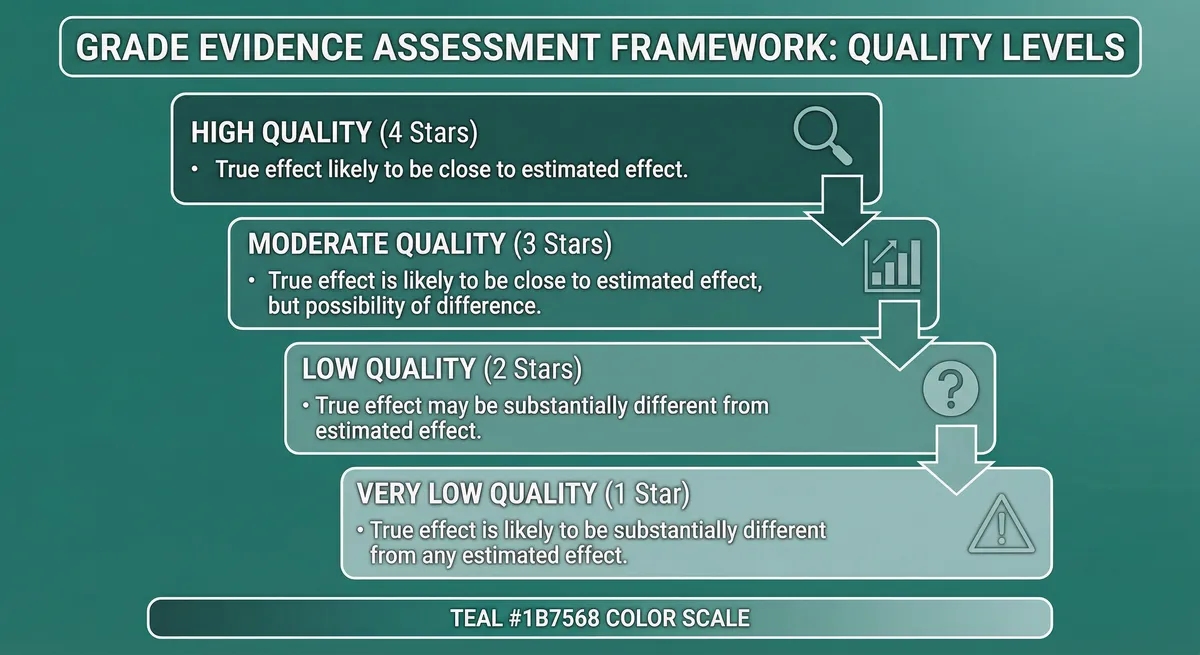
GRADE Evidence Level: High
Consistent results from well-designed RCTs or overwhelming observational evidence
FDA 510(k) Clearances: Three Cleared Suppliers
The FDA has cleared medicinal leeches through three separate 510(k) submissions, establishing a regulatory foundation for clinical use in reconstructive microsurgery. All three clearances address venous congestion in grafted or otherwise compromised tissue, but the indication wording differs: K040187 (2004) is 'an adjunct to the healing of graft tissue when problems of venous congestion may delay healing, or to overcome problems of venous congestion by creating prolonged localized bleeding'; K132958 (2014) covers skin flaps, skin grafts or other tissues with impaired venous circulation; K140907 (2015) additionally names surgical reattachments.
K040187 — Ricarimpex SAS
Cleared: June 21, 2004 · CBER tracking: BK251211
Product: Hirudo medicinalis
The original 510(k) clearance. Ricarimpex SAS (Eysines, France) is one of three FDA 510(k)-cleared suppliers serving the US market.
K132958 — Biopharm UK Ltd.
Cleared: February 19, 2014 · CBER tracking: BK251217
Product: Hirudo verbana
Second 510(k) clearance. Biopharm UK Ltd. (Hendy, Carmarthenshire, Wales) breeds H. verbana, the species used in most modern clinical research.
K140907 — Carolina Biological Supply Co.
Cleared: August 7, 2015 · CBER tracking: BK251218
Product: Hirudo verbana
Third 510(k) clearance. Carolina Biological Supply Company (Burlington, NC) provides an additional US-based supply option.
CBER Jurisdiction Transfer (December 30, 2024)
Definitive Clinical Evidence
The evidence base for medicinal leeches in reconstructive microsurgery consists of 4 systematic reviews, multiple large retrospective studies, and decades of consistent clinical experience across academic medical centers worldwide. Large randomized controlled trials in acute flap-salvage settings are difficult to conduct ethically and practically — the intervention is time-critical and the comparator is loss of viable tissue — so the evidence base is built primarily from systematic reviews and prospective and retrospective cohort series. Within those constraints, independent systematic reviews converge on a consistent efficacy profile.
| Study | Design | Population (n=) | Intervention | Key Outcome | Result |
|---|---|---|---|---|---|
| Whitaker et al. 2012 | Systematic review | All plastic/reconstructive surgery cases with venous congestion (67 publications, 1966-2009) (n=277) | Medicinal leech therapy for flap salvage and tissue replantation | Overall tissue salvage rate; complication profile | 78% salvage (216/277); 88.3% without infection vs 37.4% with infection; 49.75% transfusion rate Landmark systematic review. 21.8% overall complication rate (no separate infection rate reported). Established the definitive salvage rate benchmark. |
| Cornejo et al. 2017 | Retrospective cohort | Patients requiring leech therapy following microsurgical reconstruction at a single academic center (n=87) | Medicinal leech therapy; average 74.4 leeches per patient over treatment course | Tissue salvage rate; leech use; complications | 60.9% overall success rate (53/87); 36.7% transfusion rate (32/87); 8% infectious complications (7/87) Largest single-center retrospective study. Reported an average of 74.4 leeches per patient over an average of 4.6 days of therapy. |
| Herlin et al. 2017 | Systematic review + retrospective case series | Pedicled and free flaps with venous congestion (41 studies reviewed + own 43-patient series) (n=41 studies + 43 patients) | Medicinal leeches with ciprofloxacin + TMP-SMX prophylaxis | Flap salvage success; application protocol | Success 65–85% across reviewed studies (83.7% in the authors' 43-patient series) Optimal application every 2–8 hours for an average of 4–10 days; about half of the cases reported in the literature needed transfusion; recommended ciprofloxacin + TMP-SMX prophylaxis. |
| Hackenberger & Janis 2019 | Narrative review | Plastic and reconstructive surgery patients (n=NR) | Medicinal leech therapy for venous congestion | Indications, application, number and duration of therapy, risks | Summarizes recent literature for plastic surgery: leeches as an FDA-cleared, nonsurgical option for venous congestion; infection and bleeding are the main risks Plast Reconstr Surg Glob Open 2019;7(12):e2555 (PMID 32537302) |
| Rajaram et al. 2024 | Systematic review | Breast reconstruction patients; 18 studies (4 case series, 14 case reports); 28 patients (n=28) | Medicinal leech therapy for flap congestion; median 2 leeches/session, 3 sessions/day, 3 days | Tissue salvage rate; complication burden | 75% salvage; 81% complication rate (infection and anemia dominant) First systematic review dedicated to breast surgery. Concluded judiciously used given high complication burden. |
Why No Randomized Controlled Trials Exist
Microsurgical Applications: Salvage Rates by Indication
Medicinal leeches are used across the full spectrum of reconstructive microsurgery wherever venous congestion threatens tissue viability. Each application falls within the FDA 510(k)-cleared indication for venous congestion management in compromised tissue flaps and replantation.
Digit Replantation
68–83%
Salvage rate
Most common indication. Venous anastomosis often impossible in distal amputations (zone I/II), making leeches the primary venous outflow mechanism. Soucacos 1994: venous drainage restored with leeches in 9 of 11 replantations (digits and hands) and 15 of 18 free tissue transfers (24 of 29 patients overall).
Ear Replantation
68%
Salvage rate
Auricular veins are small, thin and fragile, so suitable veins for anastomosis are often unavailable after avulsion. Leeches are a recognized option for venous decompression when venous repair is not possible. More than 130 cases of successful ear salvage are described in the literature, with leeches used in 40 of 119 analyzable cases.
Lip & Nose Replantation
Case reports only
No pooled salvage rate
Facial subunit replantation depends on leech therapy for venous decompression. Small-caliber veins make microsurgical venous repair unreliable.
Breast Reconstruction (DIEP/TRAM)
75%
Overall salvage rate across breast surgery (Rajaram 2024; 61.5% for free flaps)
Complication rate 81.14% across the 28 patients (18 reports and series), mainly infection and anaemia; the authors note this population did not have more frequent or longer leeching than other plastic surgery. Venous outflow augmentation with the superficial inferior epigastric vein (SIEV) was associated with less fat necrosis in one retrospective DIEP series (10.0% vs 26.5%); prospective confirmation is needed.
Free Flaps (General)
78–84%
Salvage rate
Standard of care when venous thrombosis or congestion occurs postoperatively and surgical revision is not feasible or has failed. Herlin et al. (2017): 65–85% success across flap-salvage studies (83.7% in their own series).
Pedicled Flaps
81%
Salvage rate
Venous congestion in pedicled flaps (e.g., pectoralis major, latissimus dorsi) responds well to leech therapy; in a small single-centre series, tissue salvage was higher in pedicled flaps than in free flaps.
Timing: Treat Flap Compromise Early
What the timing data show
Within 24 Hours
83.7%
Salvage of compromised breast free flaps (surgical; Chang 2016)
Prompt recognition and immediate treatment. Most academic centers have nursing protocols for immediate initiation upon clinical detection of venous congestion (dark purple color, turgid tissue, brisk dark blood on pinprick).
Days 1–3
38.6%
Salvage of compromised breast free flaps (surgical; Chang 2016)
Later salvage succeeded far less often (29.4% beyond day 4). Sustained venous hypertension, interstitial edema, and thrombotic propagation damage the tissue over time.
Clinical Implications for Hospital Protocols
Because flap compromise is best treated early, institutions should maintain leech availability around the clock. EMR-integrated order sets should enable stat leech application within 30 minutes of clinical detection. Night and weekend availability is critical — venous congestion does not follow a business-hours schedule. Application frequency: every 2–8 hours; average treatment duration: 4–10 days (Herlin et al., 2017).
Hospital Adoption: Major US Academic Medical Centers
Medicinal leeches are stocked and used routinely by plastic and reconstructive surgery departments at major academic medical centers across the United States. The following institutions have published institutional protocols, case series, or are known to maintain active leech therapy programs.
| Institution | Department(s) | Primary Applications |
|---|---|---|
| Johns Hopkins Hospital | Plastic Surgery, Otolaryngology | Free flap salvage, digit replantation, ear reconstruction |
| Cleveland Clinic | Plastic Surgery, Hand Surgery | Microsurgical flap salvage, digit replantation |
| Duke University Medical Center | Plastic & Reconstructive Surgery | Free flap monitoring, breast reconstruction salvage |
| Baylor College of Medicine | Plastic Surgery, Hand & Microsurgery | Digit replantation, free tissue transfer |
| Tampa General Hospital / USF | Plastic Surgery | Free flap salvage, published institutional protocol |
| Stanford University Medical Center | Plastic & Reconstructive Surgery | Microsurgical reconstruction, breast reconstruction |
| Massachusetts General Hospital | Plastic Surgery, Orthopaedic Hand Service | Replantation, free flap salvage, composite tissue |
US Leech Supply Chain
Institutional Protocol: Standard of Care Parameters
The following protocol parameters represent consensus practice at US academic medical centers, synthesized from published institutional protocols, systematic reviews, and expert practice patterns.
| Parameter | Standard Protocol | Notes |
|---|---|---|
| Leech count per application | 1–6 leeches per session | Typically 2–3 for digit/ear; 4–6 for large free flaps; titrated to flap size and congestion severity |
| Application frequency | Every 2–8 hours | Every 2 hours initially in some protocols (reported range 2-8 hours); interval lengthened and application tapered as congestion improves; continuous clinical assessment guides frequency |
| Treatment duration | Average 4–10 days across published series (Herlin 2017); 4.6 days average, range 1–11, in the Duke series (Cornejo 2017) | Continue until venous outflow re-established (stable skin color, normal capillary refill and normal-colored pinprick bleeding; duration is an empirical clinical decision) |
| Average leeches per course | 74.4 leeches/patient (Shammas 2016, Duke series later published as Cornejo 2017) | Range: 10–200+ depending on flap size and duration; breast reconstruction courses tend to be longer |
| Antibiotic prophylaxis | Ciprofloxacin + trimethoprim-sulfamethoxazole (combination; doses per institutional protocol) | Start before first leech application; continue for at least 24 hours after the last application (published protocols vary). Because ciprofloxacin-resistant Aeromonas following leech therapy has been reported, ciprofloxacin monotherapy may be unreliable; combination prophylaxis (adding trimethoprim-sulfamethoxazole) is commonly recommended |
| Hematologic monitoring | CBC (hemoglobin/hematocrit) every 4 hours during active treatment | Transfuse pRBC if Hgb <7 g/dL (<8 g/dL with cardiac comorbidity); maintain 2 units crossmatched and available |
| EMR order set components | Leech application, antibiotic prophylaxis, CBC frequency, transfusion thresholds, flap monitoring schedule | Standardized order sets reduce medication errors and ensure protocol compliance; should include nursing education materials |
EMR-Integrated Order Sets
Cost-Effectiveness Analysis
Leech therapy is cost-effective relative to the surgical procedures it salvages. The direct cost of leeches is a small fraction of the total cost of microsurgical reconstruction, and successful salvage avoids the far greater expense of flap failure, return to the operating room, and prolonged hospitalization.
$10–30
Cost per leech
74.4
Average leeches per patient (Shammas 2016, Duke series later published as Cornejo 2017)
$750–2,200
Total leech cost per treatment course
3–7 days
Cost-efficiency cutoff in digit replantation (one digit 3 days, thumb 5, multiple digits 7)
| Study | Design | Population (n=) | Intervention | Key Outcome | Result |
|---|---|---|---|---|---|
| Cornejo et al. 2017 | Retrospective cost analysis | 87 patients requiring leech therapy after flap reconstruction or appendage replantation (Duke University, 8 years) (n=87) | Medicinal leech therapy; avg 74.4 leeches/patient | Direct cost of leech therapy vs. cost of flap failure and reoperation | approx. $750-$2,200 for leeches alone (74.4 leeches at $10-$30 each); transfusion costs additional (transfusion needed in 36.7% of patients) Leech cost is roughly $750-$2,200 per course (74.4 leeches at $10-$30 each). A free-flap return to the operating room added a mean $33,507 in hospital costs (one head and neck series). |
The Economic Case for Leech Therapy
Alternative Venous Decompression Methods
While medicinal leeches remain the standard of care, several alternative approaches to venous decompression exist. The evidence for these alternatives is of low level and does not allow firm conclusions about their effectiveness; leeches remain the only non-surgical method with a satisfactory level of evidence, and Hirudo medicinalis was FDA-cleared as a medical device in 2004 (510(k) K040187).
| Method | Mechanism | Salvage Rate | Limitations |
|---|---|---|---|
| Medicinal leeches (standard of care) | Combined mechanical blood removal + pharmacologic anticoagulation (hirudin, calin, destabilase) providing 24–48h continued bleeding | 78% (Whitaker 2012) | Aeromonas infection risk (7 of 35 patients infected, 5 with Aeromonas, in one unit's series; Whitaker 2011); transfusion requirements (50%); patient/staff aversion |
| Heparin pledgets / chemical leech | Topical heparin-soaked gauze applied to scarified tissue; local anticoagulation effect only | Limited data; reported success rates are high but come from small cohorts (e.g., 15 of 15 flaps salvaged, 7 totally and 8 partially, with LMWH injection) | No pharmacologic synergy; requires repeated scarification; less effective for deep tissue congestion |
| Mechanical leeching devices | Suction-based devices that create negative pressure for blood removal; no pharmacologic component | Insufficient clinical data | No anticoagulant effect; no continued post-application bleeding; prototype stage; no FDA clearance |
| Surgical venous revision | Microsurgical re-anastomosis of thrombosed or kinked veins; addresses the root cause when technically feasible | Variable; depends on cause | Not always technically feasible; may damage adjacent structures; failure leads to leech therapy as rescue |
Safety Considerations and Complication Management
The Primary Complication: Aeromonas hydrophila
Infection Rate
20%
7 of 35 patients, 5 with Aeromonas (Whitaker 2011)
Without prophylaxis: 2.4–20%. In that series infection was significantly more frequent without prophylactic antibiotics. Nguyen et al. (2012) observed no Aeromonas wound infection in 39 patients, an incidental finding; no prophylaxis protocol was studied.
Transfusion Rate
50%
In surgical settings
49.75% of patients required blood transfusion (Whitaker 2012). Each leech removes 5–15 mL of blood, and the wound may continue to ooze for up to 24 hours after the leech is removed.
Bleeding Management
CBC q4–8h
During active treatment
Maintain hemoglobin >7 g/dL (>8 g/dL with cardiac comorbidity). Keep 2 units pRBC crossmatched and available. Aggressive IV hydration to compensate for blood loss. Monitor coagulation panel daily.